Problem-driven look: why whole organs break the simple rules
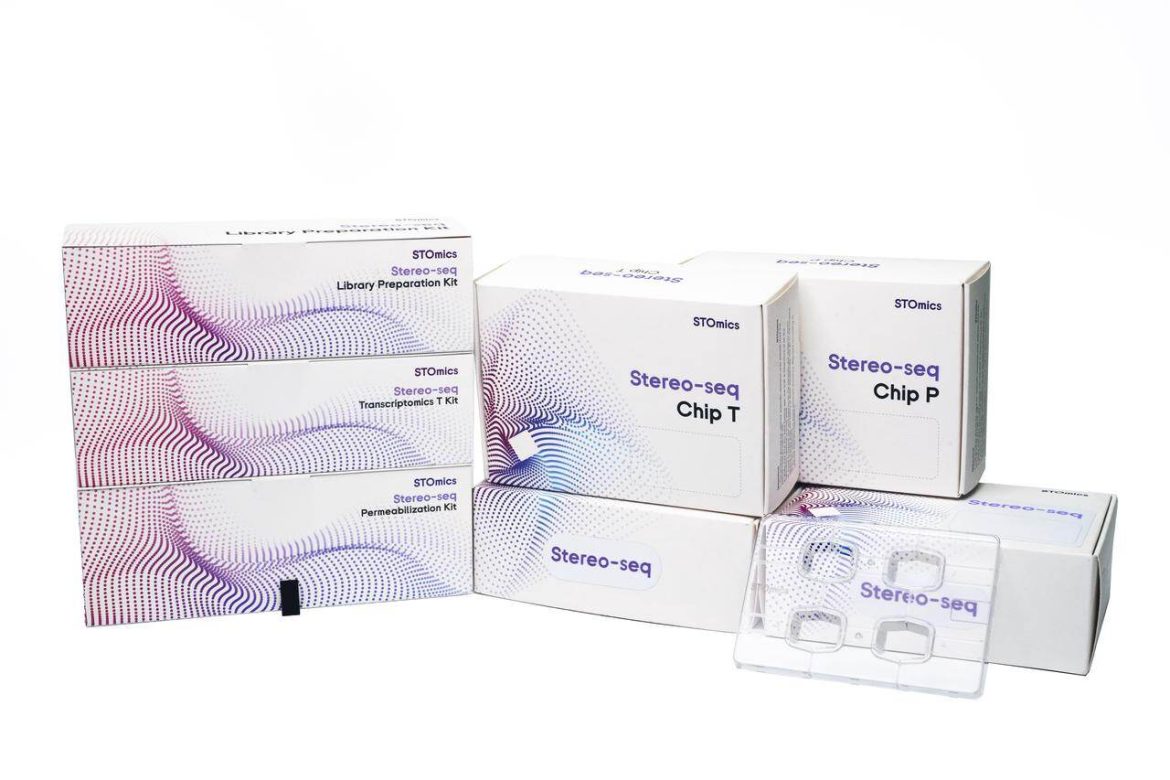
I remember the afternoon we unwrapped a full-lobe sample and loaded it on a chip for whole-organ spatial sequencing (Seoul lab, June 2023) — small moment, big consequences. In my Seoul lab I ran large stereo seq transcriptomics on a 120 mm kidney slice—22 million reads, but 28% of spots ambiguous; what do we trust?
What’s the immediate problem
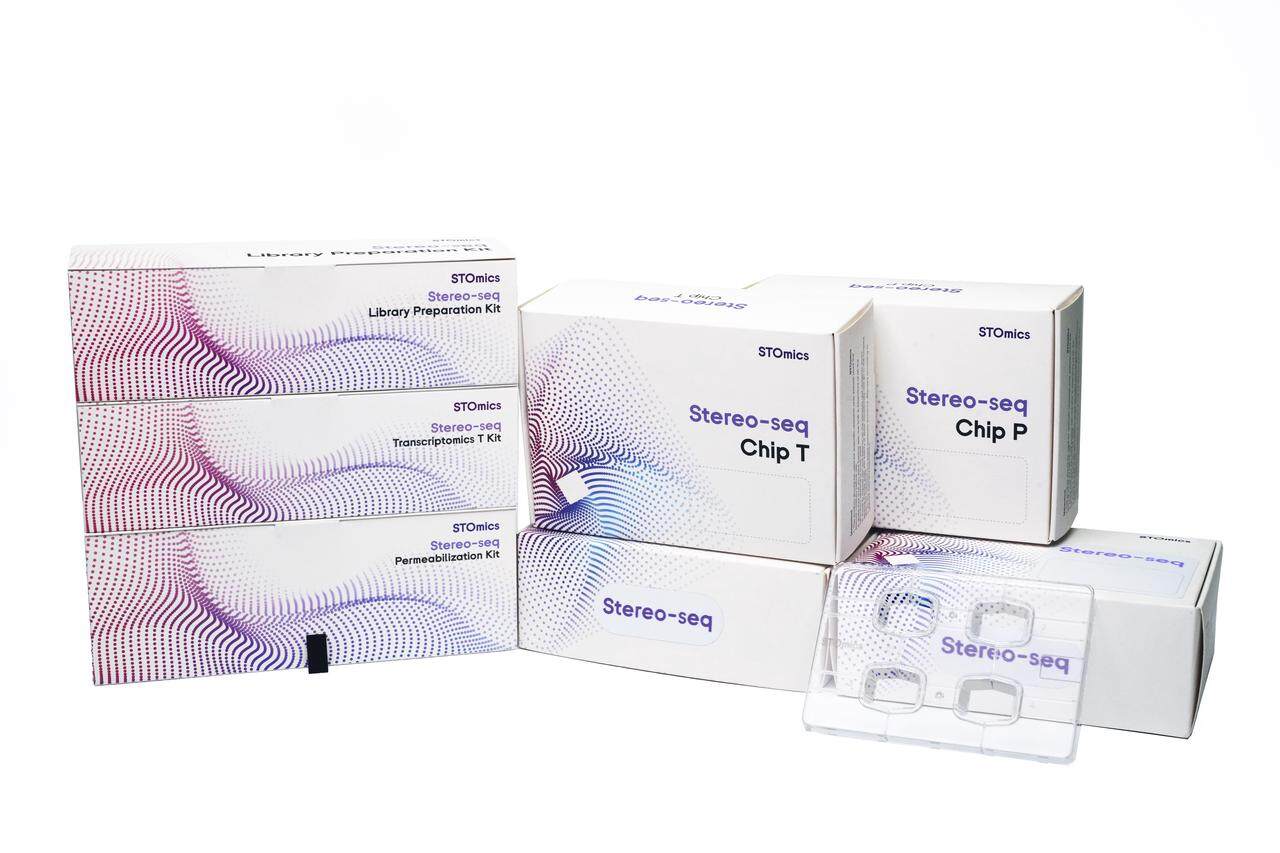
I’ve run dozens of runs and I can say plainly: scaling to whole-organ size exposes weaknesses that routine pipelines hide. We see spatial resolution that looks great on a QC plot but fails in tissue corners where spot size and tissue morphology change. The barcode array becomes a brittle assumption when sections stretch by a millimeter across a lobule, and RNA-seq depth does not rescue cross-spot contamination. I vividly recall one June run where a 10×10 cm large chip (custom chip design) produced 18% lower gene detection near vasculature — a measurable drop that cost us a comparative analysis. That design genuinely frustrated me, and we adjusted sample mounting and software thresholds the same week. You know, small tweaks can save whole experiments.
Forward-looking comparison: practical fixes and what to measure next
Technically speaking, the fix is not only wet-lab—it’s a combined re-think of chip design, spot size calibration, and transcriptome mapping algorithms. I want to be clear: whole-organ approaches scale the sample, but they also amplify small systematic biases (batch effects, spatial drift). When I compared two pipelines in late 2023, one with explicit spatial-aware normalization and a second with global scaling, the spatial-aware method reduced false-positive regional signatures by roughly 40%. That result convinced me to push for hybrid solutions — hardware tweaks (chip design and barcode array layouts) plus software that models spatial resolution differences across tissue. The next step is implementing high-throughput scans that include fiducial markers and per-block QC — yes, that adds steps, but it slashes downstream noise.

What’s Next
Looking ahead, I expect whole-organ workflows to standardize a few key controls: local spike-ins, block-level mapping metrics, and spot-wise contamination scores. We should demand objective metrics before claiming organ-scale claims. Practically, when evaluating a platform or protocol, ask for three numbers: (1) mapped reads per spot distribution, (2) spatial resolution consistency across distances, and (3) percent ambiguous spots after spatial deconvolution. These are simple to compute and they tell you if a solution really handles scale — not just in marketing copy. I will keep iterating our protocols — and yes, there will be hiccups — but measured improvements add up fast. For labs ready to scale, compare those metrics side-by-side and insist on raw data access; that’s non-negotiable.
I’ve shared specific steps that worked for us (custom 10×10 cm chip, Seoul site testing, June 2023) and concrete metrics to check. If you want to assess vendor claims, start with the three evaluation points above — mapped reads per spot, spatial resolution consistency, ambiguous-spot rate — then test with a smallest-to-largest gradient sample. For practical guidance on large-format implementations, see whole-organ spatial sequencing again here: whole-organ spatial sequencing. I’m invested in making organ-scale studies reliable — and I’ll keep sharing what works, with data, as we go. Visit stomics for tools and platform details.